



19 May Acne Explained: Causes, Types and Treatment Evidence
Acne: Causes, Types and What Treatments Can Do
By Dr Rachel Ho | Updated August 2026
Acne is one of the most common skin conditions I treat in clinical practice, compounded significantly by Singapore’s heat and humidity, which tends to worsens oily skin. While the natural instinct for many patients is to aggressively scrub, peel, and mattify away the excess oil, these harsh measures end up traumatising the skin barrier and trigger a compensatory cycle of inflammation. Let this comprehensive guide to acne and pimples take you through why acne develops and the evidence based skincare and treatments for treatment and prevention.
Acne treatment at a glance
The table below summarises how acne treatment is usually matched to severity and pattern. Age, pregnancy, skin sensitivity, pigmentation risk, previous treatment and the psychological effect of acne can all change the final plan3,4, 7.
Acne treatments at a glance
FAQ about acne treatments in Singapore
| Acne pattern or severity | Treatments commonly considered | Where procedures may fit | Important points |
|---|---|---|---|
| Blackheads and whiteheads | A topical retinoid is often the foundation. Benzoyl peroxide, azelaic acid or salicylic acid can be used.1,3,4 | Superficial chemical peels may help persistent congestion in selected patients. | Treatment should be applied to the acne prone area rather than only to visible spots because microcomedones form before pimples can be seen. |
| Mild inflammatory acne | A topical retinoid combined with benzoyl peroxide addresses follicular blockage and inflammation.3,4 | LED light or selected chemical peels may be used as supportive treatments. | Improvement usually takes several weeks. Introducing active ingredients gradually can reduce irritation. |
| Moderate inflammatory acne | Combination topical treatment remains important. A limited course of oral doxycycline or another suitable antibiotic may be considered.3,4 | LED light and chemical peels may complement medical treatment in suitable patients. | Oral and topical antibiotics should be combined with benzoyl peroxide where appropriate. Prolonged antibiotic monotherapy is discouraged. |
| Hormonal or adult female acne | A topical retinoid, benzoyl peroxide or azelaic acid may help. Selected women may benefit from spironolactone or a suitable combined oral contraceptive.3,4 | Procedures may help individual persistent lesions or associated pigmentation, but they do not correct the hormonal driver. | Menstrual pattern, pregnancy plans, blood pressure, medical history and other medicines should be reviewed. |
| Recurring acne from the same follicles | Medical treatment remains the starting point. Selective sebaceous gland ablation may be considered for repeatedly inflamed follicles.9 | Insulated microneedle radiofrequency can deliver energy selectively to the sebaceous gland associated with a recurrent lesion. | Evidence is more limited than for established topical and oral medication. It should be used selectively rather than as a universal acne treatment. |
| Deep nodules or cyst like lesions | Early medical assessment is important. Oral medication, including isotretinoin when appropriate, may be needed.3,4 | An intralesional corticosteroid injection may rapidly reduce inflammation in a selected large lesion at high risk of scarring. | Deep acne has a greater risk of permanent scarring. Squeezing or repeatedly injecting lesions does not control the wider acne tendency. |
| Severe, widespread or scarring acne | Oral isotretinoin is strongly recommended for suitable patients with severe, scar forming or treatment resistant acne.3,4 | Procedures are usually secondary to controlling active disease. Scar treatment can be planned once new inflammatory lesions are stable. | Pregnancy prevention and medical monitoring are essential. Relapse can occur, and some patients require maintenance treatment. |
| Back, chest or shoulder acne | Topical benzoyl peroxide, topical retinoids and systemic treatment may be used according to extent and severity. | LED light, selected peels or other procedures may be considered when practical. | Truncal acne can be difficult to reach and may require a treatment format that is easy to apply consistently. |
| Brown marks after acne | Daily sunscreen and ingredients such as azelaic acid or a suitable retinoid may help while active acne is controlled. | Chemical peels and selected Q switched laser treatments may be considered for persistent post inflammatory hyperpigmentation. | Brown marks are pigment changes rather than structural scars. Excessive irritation can deepen pigmentation in Asian skin. |
| Red marks after acne | Control of active inflammation, gentle skincare and sun protection are important. | Selected vascular or light based treatments may help persistent redness after assessment. | Post inflammatory erythema differs from brown pigmentation and requires a different treatment approach. |
| Depressed or raised acne scars | Active acne should be controlled before a full scar treatment programme begins. | Subcision, fractional resurfacing, RF microneedling, scar specific procedures or injections may be selected according to scar type. | Acne scars involve structural changes in the skin. Q switched pigment lasers and ordinary facials cannot correct tethered or deep scars. |
What is acne?
Acne vulgaris is a chronic inflammatory condition of the pilosebaceous unit, which consists of a hair follicle and its sebaceous gland. This can result in blackheads, whiteheads, papules, pustules, nodules and deep cyst-like lesions on the face, chest, shoulders and back1,2.
Acne affects about 9% of the global population and up to 85% of people aged 12 to 24 years. Around half of people aged 20 to 29 may continue to experience acne. In Singapore, one community study found acne in approximately 88% of adolescents aged 13 to 19 years1,7.
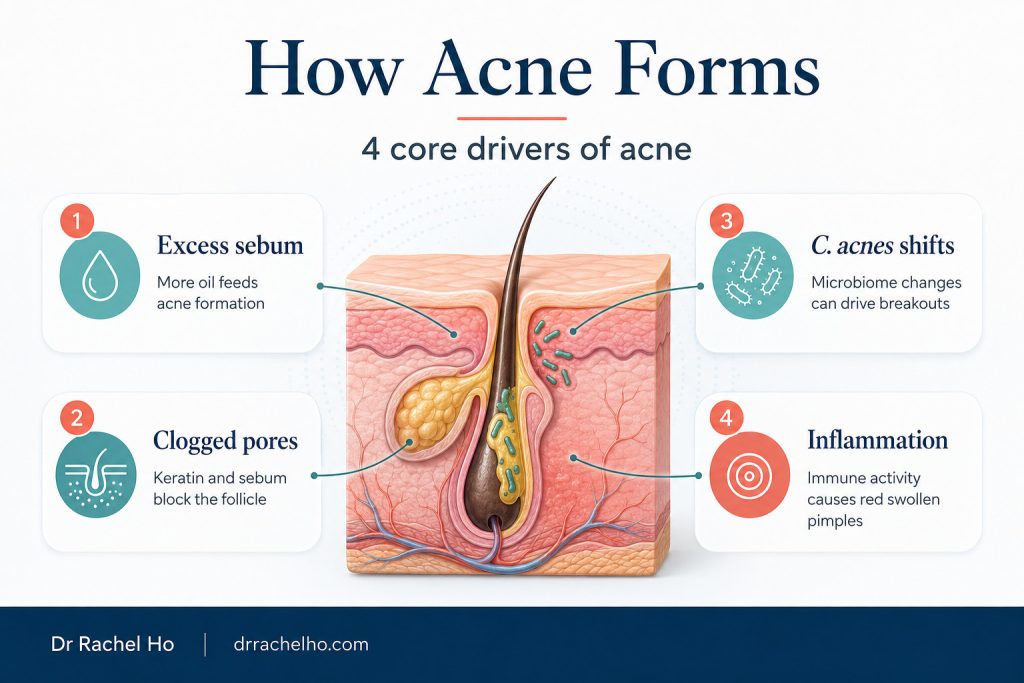
How acne forms. Acne develops through excess sebum, follicular blockage, microbiome changes involving Cutibacterium acnes, and inflammation. Understanding these four drivers helps explain why acne treatment often needs more than one approach.
How does acne form?
Every form of acne or pimple begins with the pilosebaceous unit. Four interacting processes result in the formation of pimples, and effective acne treatment usually needs to address these different pathways2,3.
Excess sebum
Androgens stimulate sebaceous gland activity, while local androgen sensitivity and insulin like growth factor 1 (IGF-1) can influence oil production. Changes in sebum composition may also encourage follicular cell growth and inflammation2.
This explains why oily skin and acne often occur together. Contrary to popular belief, a person can have dehydrated or sensitive skin and still develop acne because follicular blockage and inflammation remain active.
Follicular hyperkeratinisation
The microcomedone is the earliest acne lesion. Retained keratin cells and sebum form a microscopic follicular plug that can later become a blackhead, whitehead or inflamed pimple1,2.
Topical retinoids are useful partly because they reduce this abnormal retention of skin cells inside the follicle. Their role extends beyond drying an existing pimple, since they also help prevent future microcomedones.
Cutibacterium acnes bacterial infection
Cutibacterium acnes is part of the normal skin microbiome, so acne is more complex than a simple bacterial infection. Changes in the balance of bacterial strains, rather than the mere presence of the organism, appear to promote TLR2 and Th17 immune signalling5.
Research into the bacterial enzymes HylA and HylB illustrates this distinction in acne. HylA from acne associated strains promoted inflammation in a mouse model, while the HylB variant associated with healthy skin had a more anti-inflammatory effect. These findings are scientifically interesting, although they are not yet used as a routine clinical test6.
Inflammation and scarring
The combination of congestion and bacterial infection result in a build up of inflammation. Immune cells and inflammatory enzymes can damage tissue around an affected follicle. Matrix metalloproteinases contribute to breakdown of the dermal matrix, resulting in atrophic or depressed scars2,5.
What causes acne or makes it worse?
Genes, puberty, androgen activity, oily skin and family history influence acne risk. Stress, friction, occlusion, oily hair products and certain medicines like steroids can aggravate existing disease2,7.
Diet matters for some people, although this does not hold for some patients. Lower glycaemic load diets have improved acne in some studies, while other trials found less convincing differences. Research concerning whey protein is also mixed, with both positive associations and a recent randomised trial that did not show clear worsening15,16.
Singapore’s heat and humidity can add sweat, friction and occlusion, especially beneath helmets, masks, caps and tight sportswear. Poor hygiene is often faulted as the cause of acne, leading to patients to compensate with excessive washing and scrubbing that worsens irritation and post inflammatory pigmentation instead7.
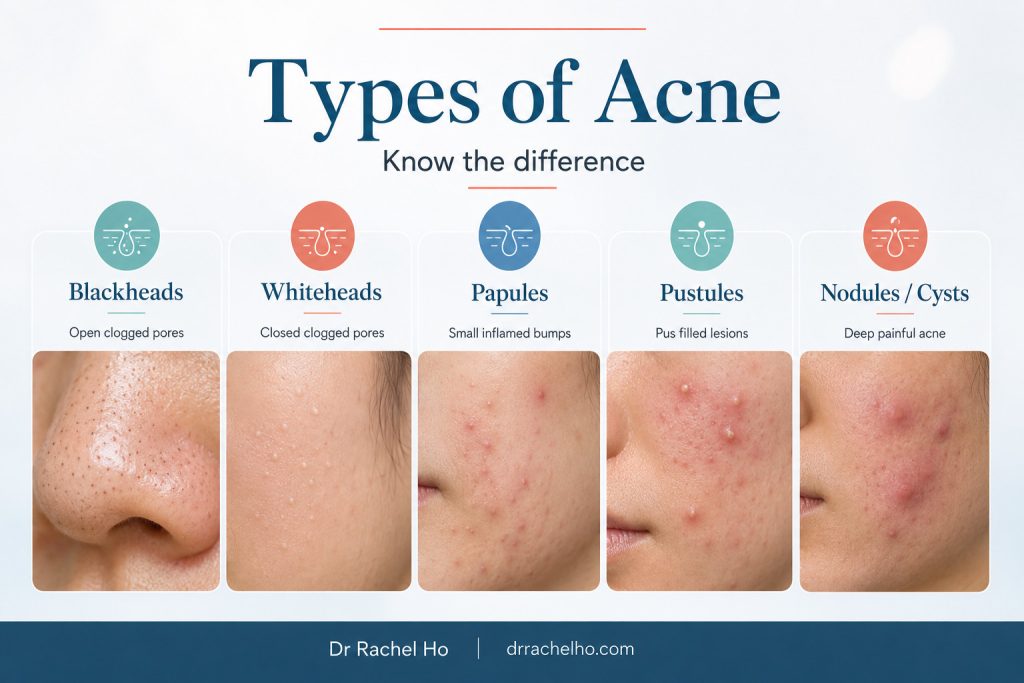
Types of acne at a glance. Blackheads, whiteheads, papules, pustules and nodules do not behave the same way, which is why the best acne treatment in Singapore depends on the lesion type.
What type of acne do you have?
Comedonal acne consists mainly of blackheads and whiteheads. Papulopustular acne produces inflamed red bumps and pus filled lesions, while nodular or cystic acne forms deeper painful lesions with a greater risk of scarring1,3.
Adult female acne often appears along the jawline and lower face, but its location alone does not prove a hormonal cause. Truncal acne affects the chest, shoulders and back, while Malassezia folliculitis, bacterial folliculitis, perioral dermatitis and rosacea can resemble acne and require different treatment.

Acne treatments at a glance. Mild acne may respond to topical treatment, while moderate inflammatory acne may require combination therapy and severe or scarring acne may need earlier medical review and isotretinoin.
What is the best acne treatment in Singapore?
The best acne treatment is the simplest plan that controls current disease, prevents new lesions and reduces scarring without unnecessary side effects. Lesion type and severity guide the choice more reliably than trending skincare, device or treatment package3,4.
Mild comedonal acne
A topical retinoid is often the most useful foundation because it normalises follicular cell turnover and helps prevent new microcomedones. Benzoyl peroxide, azelaic acid or salicylic acid may be added according to inflammation, post acne pigmentation and skin tolerance1,3.
Related blogposts:
Retinol for Skin: Benefits, Percentage and How to Use It
Retinol vs Retinal vs Tretinoin: Which Should You Use?
Aklief (Trifarotene): 4th Generation Retinoid for Acne
Mild to moderate inflammatory acne
A topical retinoid combined with benzoyl peroxide targets both follicular blockage and inflammation. Topical antibiotics should be paired with benzoyl peroxide rather than used alone, since prolonged antibiotic monotherapy encourages resistance3,4.
Azelaic acid can be particularly useful when inflammatory acne and post inflammatory hyperpigmentation occur together. Its tolerability still varies, so frequency and the rest of the skincare routine need to be adjusted for sensitive skin.
Related blogpost:
Azelaic Acid Singapore: Benefits, Products and How to Use It
Moderate to severe inflammatory acne
More extensive inflammatory acne may require an oral antibiotic such as doxycycline alongside topical treatment. The 2026 EuroGuiDerm update advises that systemic antibiotics should generally be limited to about 3 months, with longer courses reserved for exceptional circumstances4.
Topical maintenance treatment remains important during and after an antibiotic course. The purpose is to control acne through several mechanisms while reducing unnecessary exposure to systemic antibiotics.
Hormonal and adult female acne
Selected women may benefit from spironolactone or an appropriate combined oral contraceptive, especially when acne follows a menstrual pattern or occurs with other features of androgen activity. Pregnancy plans, blood pressure, concurrent medicines and medical history should be evaluated before starting on hormone treatments for acne3,4.
Severe, nodular or scarring acne
Oral isotretinoin acts across several acne pathways and is strongly recommended for severe, scar forming or treatment resistant acne. It may also be appropriate when acne creates a substantial psychological burden3,4.
Related blogposts:
Isotretinoin Singapore: Benefits, Side Effects and Safety
What TikTok Gets Right and Wrong about Acne Medications
A large painful pimple
An intralesional corticosteroid injection can reduce inflammation, especially in pimples that have a high risk of scarring. It is symptomatic management and does not treat the pathogenesis of acne, so ongoing acne treatments are still important3.

Where in clinic acne treatments fit. Selective sebaceous gland ablation, LED light, chemical peels and Q switched laser can complement acne care in selected patients, but they work best when matched to the right indication.
Where do in clinic acne treatments fit?
In-clinic treatments can help recurrent lesions, widespread congestion or post acne pigmentation, and they can complement prescription treatment. The 2024 American Academy of Dermatology guideline found insufficient evidence to make broad formal recommendations for most lasers, light devices and chemical peels, so these treatments should be chosen as targeted adjuncts rather than automatic first line care3.
Selective sebaceous gland ablation
Selective sebaceous gland electrothermolysis delivers radiofrequency energy through an insulated microneedle to a sebaceous gland associated with a recurrent lesion. A prospective randomised study reported improvement after three sessions, although the evidence base remains smaller than that supporting established topical and oral acne medication9.
My clinic guide to RF Microneedling for Acne: Selective Sebaceous Gland Ablation explains why this approach is most relevant when inflammatory acne repeatedly returns from identifiable follicles. It also distinguishes targeted sebaceous gland treatment from fractional RF microneedling used for acne scars.
LED light treatment
Blue and red LED light can support inflammatory acne through antimicrobial and anti inflammatory effects, with little downtime. LED is therefore best viewed as supportive treatment for acne. Please read LED Light Treatments in Singapore for a complete guide to LED light therapy
Chemical peels
Superficial salicylic acid, glycolic acid and related peels may help comedones, surface oiliness and selected post acne marks. A systematic review of 12 randomised trials found that commonly studied peels appeared similarly useful for mild to moderate acne, but the evidence could not establish one universally superior peel11.
Peel depth, barrier condition and pigment tendency matter in Asian skin because excessive irritation can leave darker marks. The Chemical Peel Treatments in Singapore guide explains how chemical peels can improve acne and post inflammatory hyperpigmentation
Q switched laser treatment
Q- switched laser treatment has a clear role for treating acne and post-inflammatory hyperpigmentation. My clinic’s page to Q Switched Laser Treatment in Singapore page explains its pigment focused uses, limitations and risks.
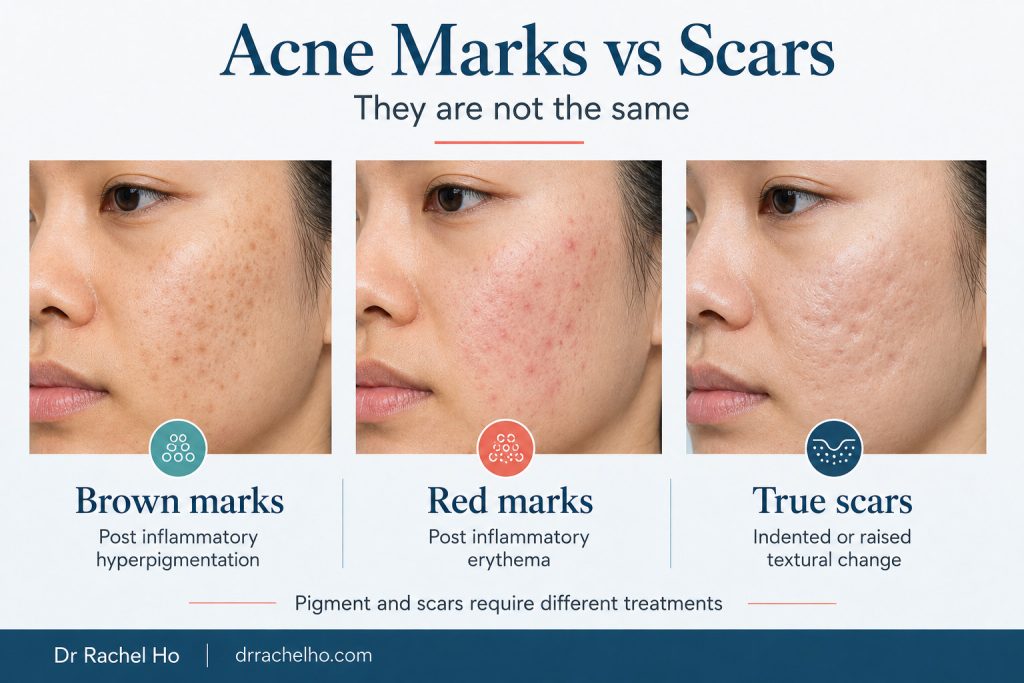
Acne marks and acne scars are different conditions. Brown marks, red marks and true textural scars each require a different treatment approach, especially in Asian skin where post inflammatory pigmentation is common.
Acne treatment for Asian skin
Inflammation in Asian skin can leave post-inflammatory hyperpigmentation long after a pimple has resolved. Early control of active acne, gentle barrier care and daily sunscreen help reduce the cycle in which each new breakout creates another persistent brown mark7.
Brown marks, red marks and depressed acne scars are often the sequelae of acne, and are due to different pathologies. The Skin Longevity Clinic has separate guides to PIH Treatment in Singapore and Acne Scar Treatment in Singapore because their treatment mechanisms and outcomes differ.
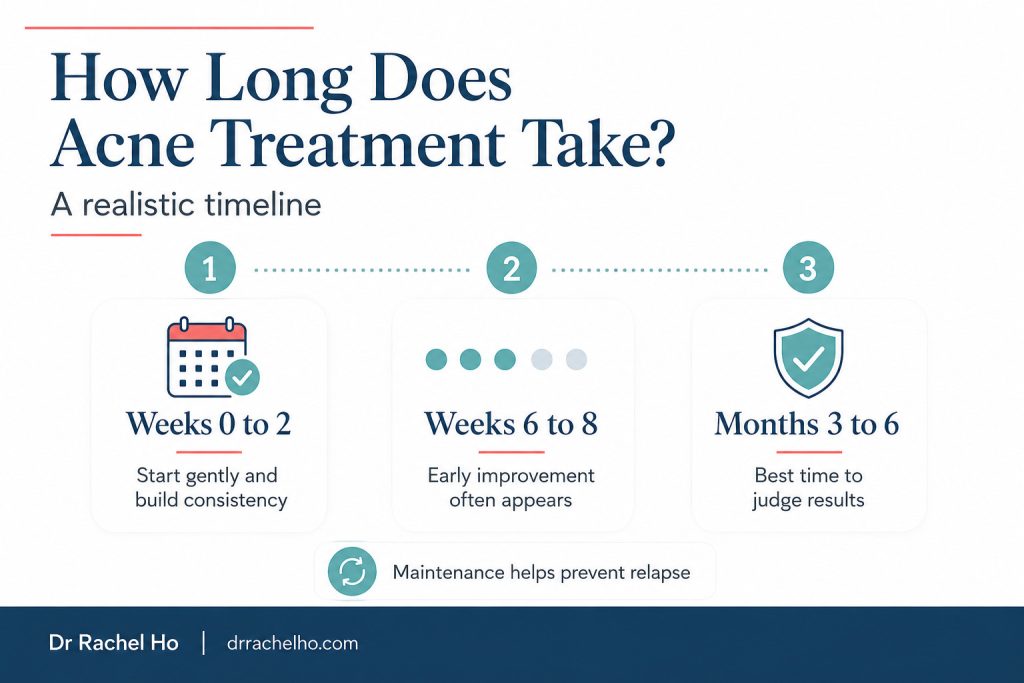
How long does acne treatment take to work. Early improvement often appears after several weeks, while a fair assessment usually takes three to six months. Consistency and maintenance matter.
How long does acne treatment take to work?
Early improvement often takes about 6 to 8 weeks, while 3 to 6 months may be needed to judge a treatment plan properly. Stopping after a few days because new lesions still appear is a common reason why acne treatments and medications seem to fail1,3.
Maintenance treatment also matters because the triggers for acne can be ongoing (e.g. menstrual cycle) and recur.
What is new in acne treatment in 2026?
The 2026 EuroGuiDerm update strengthened guidance on limiting systemic antibiotics, using isotretinoin for severe disease and considering hormonal treatment or spironolactone in suitable women. It also reviewed newer topical options such as trifarotene and clascoterone, while noting that direct comparisons with established treatments remain limited4.
Acne vaccine research has also advanced. HylA targeted vaccination reduced inflammation in mice, while a 2026 inactivated whole cell C. acnes vaccine generated antibodies and reduced inflammation and bacterial burden in a rat model6,13.
As of August 2026, Phase 1 and Phase 2 studies are evaluating an mRNA acne vaccine candidate in adults, and an adolescent safety study has also been registered. These trials have yet to establish clinical benefit, and no acne vaccine has been approved14.. I’ll be updating this blogpost with more updates as these developments occur.

When to see a doctor for acne. Deep painful acne, early scarring, widespread breakouts or failure of over the counter treatment are good reasons to seek medical assessment early in Singapore.
When should you see a doctor for acne in Singapore?
Medical review is advised when acne is deep, painful, widespread, leaving scars or failing to improve after a consistent over the counter routine. Sudden severe adult onset, irregular periods, excess facial hair, pregnancy, unusual itchy bumps or a significant effect on confidence and mood also deserve assessment.1,3,7.
Earlier control can be simpler than treating depressed acne scars later. A useful consultation identifies the acne type, distinguishes active lesions from marks and scars, reviews previous treatment and agrees on a plan that the patient can realistically continue.
Dr Rachel Ho’s clinical perspective on acne treatments in Singapore
In my clinical practice, effective acne treatment is an exercise in precision. The underlying biology, skin type, acne type and severity are highly variable among my patients. Each patient requires individualised prescription and treatment plans. For patients who also suffer from depressed acne scars, the priority should be managing the active breakouts and inflammation before embarking on scar treatment.
Frequently asked questions about acne treatment in Singapore
What is the best acne treatment in Singapore?
The best acne treatment depends on whether the acne is comedonal, inflammatory, hormonal, nodular or scarring. Mild disease often responds to topical medications with in-clinic treatments, while severe or scar forming acne may require early isotretinoin or treatments that ablate the sebaceous gland3,4.
Why do I have acne despite washing my face?
Acne is NOT due to a lack of hygiene. Acne develops inside the pilosebaceous follicle through sebum production, follicular blockage, microbial changes and inflammation. Cleansing removes surface oil and debris, but washing more aggressively does not correct all four pathways and may irritate the skin1,2.
Can acne be cured permanently?
Acne can often be controlled very well and may enter long periods of remission. Hormonal activity, untreated follicles and maintenance needs vary, so a cure is not certain unless the affectedsebaceous glands are ablated.
Can lasers cure acne?
Lasers may reduce inflammation, sebaceous activity or post acne pigmentation in selected patients, depending on the device and treatment protocol3,12.
Does sugar or whey protein cause acne?
A higher glycaemic diet may aggravate acne in some people, while the association with whey protein differs between studies and individuals. Diet can be reviewed when there is a convincing personal pattern, but dietary changes should not replace treatment for persistent, painful or scarring acne15,16.
Are post acne brown acne marks permanent scars?
Brown post acne marks are usually post inflammatory hyperpigmentation rather than depressed scars. They can fade with treatments like pico lasers and chemical peels, although repeated inflammation and ultraviolet exposure may make them last longer7.
Can Singapore’s humidity worsen acne?
Heat and humidity do not create acne on their own, but sweat, friction and occlusion may aggravate existing acne. Promptly changing out of tight or sweaty clothing and using a gentle, non occlusive routine may help reduce these triggers7.
Is an acne vaccine available?
An acne vaccine is not available for routine treatment. Early human mRNA vaccine trials are under way, while several other vaccine approaches remain at the animal study stage6, 13, 14.
Conclusion on acne treatments Singapore
Effective acne treatment begins with the correct diagnosis and a plan matched to severity, biology and scarring risk. Medication remains the foundation for many patients, while selective sebaceous gland ablation, LED light, chemical peels and Q switched laser treatment can be useful when they address a clearly defined part of the problem.
A measured plan usually produces better results than repeatedly changing products or choosing a procedure because it is new. Early control also reduces pigmentation, scarring and the emotional burden that can persist long after a breakout settles.
References
- Eichenfield DZ, Sprague J, Eichenfield LF. Management of Acne Vulgaris: A Review. JAMA. 2021;326(20):2055 to 2067.
- Moradi Tuchayi S, Makrantonaki E, Ganceviciene R, et al. Acne vulgaris. Nature Reviews Disease Primers. 2015;1:15029.
- Reynolds RV, Yeung H, Cheng CE, et al. Guidelines of care for the management of acne vulgaris. Journal of the American Academy of Dermatology. 2024;90(5):1006.e1 to 1006.e30.
- Nast A, Al Wattar BH, Beylot Barry M, et al. Update of the EuroGuiDerm evidence based guideline for the treatment of acne: Short version. Journal of the European Academy of Dermatology and Venereology. 2026;40:1162 to 1172.
- Mias C, Mengeaud V, Bessou Touya S, Duplan H. Recent advances in understanding inflammatory acne: Deciphering the relationship between Cutibacterium acnes and the Th17 inflammatory pathway. Journal of the European Academy of Dermatology and Venereology. 2023;37 Suppl 2:3 to 11.
- Hajam IA, Katiki M, McNally R, et al. Functional divergence of a bacterial enzyme promotes healthy or acneic skin. Nature Communications. 2023;14:8061.
- Oon HH, Wong SN, Aw DCW, et al. Acne management guidelines by the Dermatological Society of Singapore. Journal of Clinical and Aesthetic Dermatology. 2019;12(7):34 to 50.
- Mavranezouli I, Daly CH, Welton NJ, et al. A systematic review and network meta analysis of topical pharmacological, oral pharmacological, physical and combined treatments for acne vulgaris. British Journal of Dermatology. 2022;187(5):639 to 649.
- Ahn GR, Kim JE, Kim JM, et al. Selective sebaceous gland electrothermolysis using a minimally invasive radiofrequency device for acne treatment. Lasers in Surgery and Medicine. 2020;52(5):396 to 404.
- Scott AM, Stehlik P, Clark J, et al. Blue light therapy for acne vulgaris: A systematic review and meta analysis. Annals of Family Medicine. 2019;17(6):545 to 553.
- Chen X, Wang S, Yang M, Li L. Chemical peels for acne vulgaris: A systematic review of randomised controlled trials. BMJ Open. 2018;8:e019607.
- Maghsoodloo D, Jafarzadeh A, Ghassemi M, et al. Comparison of Q switched versus long pulsed fractional 1064 nm Nd:YAG laser in the treatment of active facial acne: A pilot, double blind, randomised, controlled, split face study. Health Science Reports. 2026;9(4):e72354.
- Lu T, Yang J, Yang D, et al. Establishment of a dynamic ear inflammation model in rats for acne vulgaris and evaluation of adjuvanted inactivated Cutibacterium acnes based vaccines efficacy. Vaccines. 2026;14(2):124.
- ClinicalTrials.gov. Studies of an acne mRNA vaccine candidate in adults with moderate to severe or mild acne, and a registered adolescent safety study. NCT06316297, NCT07013747 and NCT07756957.
- Smith RN, Mann NJ, Braue A, et al. A low glycaemic load diet improves symptoms in acne vulgaris patients: A randomised controlled trial. American Journal of Clinical Nutrition. 2007;86(1):107 to 115.
- Sompochpruetikul K, Khongcharoensombat T, Chongpison Y, et al. Whey protein and male acne: A double blind, randomised controlled trial. Journal of Dermatology. 2024;51(7):1022 to 1025.

Hanna Rice
Posted at 18:18h, 12 DecemberI appreciate your creativity and the effort you put into every post. Keep up the great work!
Cain N. K. Parrish
Posted at 20:45h, 11 DecemberWow, this blogger is seriously impressive!
Carson Knapp
Posted at 03:48h, 15 AugustSome of them have a lot of writing mistakes, which I find very annoying. On the other hand, I will definitely come back again.
Abigail Hess
Posted at 13:39h, 12 AugustI have no clue how I stumbled into this website, but I always thought this post was excellent.
Laura Moran
Posted at 22:10h, 11 AugustNaturally like your website but you need to check the spelling on many of your articles. I was excited to find this website on Bing, as it was precisely what I needed.
Jackson English
Posted at 02:36h, 29 JulyI like how hard you’ve worked on this, and thanks for all the good material.
Jaeden Cooley
Posted at 09:56h, 28 JulyAlso, thanks for letting me say something.
Matias Valenzuela
Posted at 09:28h, 27 JulyAlso, thanks for letting me say something.
Nikhil Kerr
Posted at 15:30h, 24 JulyAwesome! Its genuinely remarkable post, I have got much clear idea regarding from this post
George Nunez
Posted at 05:16h, 23 JulyThis is the first time I’ve stopped by, and I’m glad to see everything in one place.
merle norman anti aging complex night cream review
Posted at 05:01h, 11 JulyI really admire your blog-writing approach.