



23 Dec Chemical Peel Review: Benefits, Risks and Results
The Truth About Chemical Peels: Benefits, Risks and Results
A chemical peel is a controlled skin-resurfacing procedure that uses specific acid solutions to accelerate skin cell turnover, exfoliate damaged outer layers, and address targeted concerns like acne, post-inflammatory hyperpigmentation, uneven texture, and subtle fine lines¹,². Chemical peels are broadly classified by their depth of penetration: superficial, medium-depth, or deep. This classification of chemical peels according to their depth determines the degree of improvement, expected downtime, and potential risk profile of the peel¹,³.
In this clinical chemical peel review, I will break down how different chemical peel agents work, examine what current scientific evidence says about their efficacy for acne and pigmentation, and outline key safety considerations especially for Asian and darker skin tones. I hope that this blogpost can give you a realistic perspective on chemical peels and know whether chemical peels are appropriate fora long-term skin health plan.

Administering a chemical peel for my patient in The Skin Longevity Clinic.
How does a chemical peel work?
At a cellular level, a chemical peel induces a controlled chemical exfoliation within the epidermis (the outermost skin layer) and, depending on the formulation, into the dermis underneath¹,². This reaction triggers a natural healing response that drives tissue remodeling, cell renewal, and collagen synthesis¹,².
However, a chemical peel’s actual depth and performance are determined by several variables: the specific acid molecule, concentration, pH level, total contact time, skin preparation, and application technique²,³. Focusing solely on acid concentration gives an incomplete picture of how a treatment will perform clinically.

Superficial chemical peels act within the epidermis, medium depth peels extend into the papillary dermis, and deep peels reach the reticular dermis¹,³. Treatment depth influences the indications, recovery and risk profile¹,³.
Superficial, medium depth and deep chemical peels
Superificial VS medium VS deep chemical peels
| Peel depth | Where it acts | Main treatment considerations |
|---|---|---|
| Superficial | Within the epidermis | Selected comedonal acne, mild superficial pigmentation, rough skin texture, and fine surface lines¹,³ |
| Medium depth | Through the epidermis into the papillary dermis (upper dermal layer) | Pronounced sun damage, stubborn pigmentary changes, and dynamic wrinkles; requires longer downtime¹,³ |
| Deep | Into the reticular dermis (deeper dermal layer) | Severe photoaging and deep rhytides; demands strict medical monitoring and extensive recovery time¹,² |
Superficial peels typically utilise alpha hydroxy acids (AHAs like glycolic, lactic, and mandelic acids), beta hydroxy acids (BHAs like salicylic acid), or pyruvic acid, often blended for synergistic effects³. Medium-depth treatments frequently incorporate trichloroacetic acid (TCA), sometimes combined with glycolic acid or Jessner’s solution³.
Deep phenol peels, on the other hand, carry a different systemic risk profile, which has made deep phenol peels unpopular in Singapore¹. Because phenol can be absorbed into the bloodstream and potentially impact cardiac rhythm as well as liver and kidney function, these procedures require specialised medical monitoring and facility protocols for patient safety⁴.
How do the different peeling acids compare?
Glycolic, lactic, and mandelic acids belong to the Alpha Hydroxy Acid (AHA) family, whereas salicylic acid is a Beta Hydroxy Acid (BHA)². Because salicylic acid is lipid-soluble, it can dissolve through sebum to clear clogged pores, making it particularly effective for comedonal acne and oily skin types³. For a read about popular salicylic acid skincare, please see my review Salicylic Acid for Acne: Benefits, Cleansers and Serums.
TCA (Trichloroacetic Acid) is highly versatile and can be used for full-face light resurfacing or applied as a targeted, high-concentration focal treatment for individual deep scars³. Targeted focal TCA applications is known as a “TCA cross peel” and is different from applying high-strength TCA across the entire face³.
Modern professional peeling formulations often combine multiple active acids into proprietary blends or layered protocols⁵,¹⁶. While these multi-acid formulations offer versatile benefits, simply combining more acids does not necessarily make a product more effective or better tolerated by sensitive skin⁵,⁶.
For a detailed comparison with daily at-home exfoliants, read my comprehensive guide to acids in skincare and chemical exfoliation. While cosmetic products and clinical treatments may share similar ingredient names, their concentration, pH levels, and depth of action usually differ significantly².
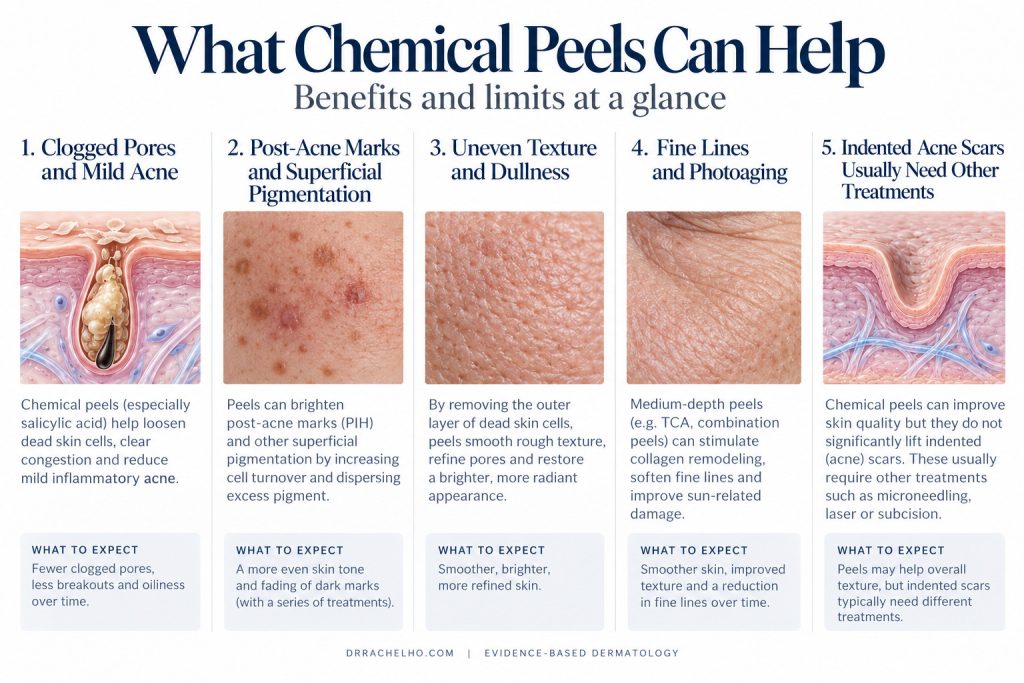
Chemical peels may help selected acne, superficial pigmentation, rough texture and fine lines¹,³. Indented acne scars involve structural changes and often require a different treatment approach, including assessment for focal scar procedures⁹.
Do chemical peels work for acne?
Chemical peels can be effective treatment for mild to moderate acne, particularly when clogged pores, whiteheads, and blackheads predominate⁵,⁶.
A comprehensive systematic review evaluated 12 randomized controlled trials involving 387 participants⁶. While several peeling regimens yielded visible improvements, the underlying studies varied widely in methodology and ranged from very low to moderate quality⁶.
In my clinic, chemical peels are used to treat as part of a broader but personalised acne management strategy that includes skincare, hormonal evaluations, medications and in-clinic treatments. If you are dealing with persistent, painful acne or breakout of that scar,a medical evaluation is essential. For a more in-depth read to acne, please refer to my guide to adult female acne and acne assessments in my clinic.
Can chemical peels improve pigmentation?
Chemical peels are evidenced for treating dark spots, however the prognosis and results are dependent on the diagnosis. Post inflammatory hyperpigmentation, melasma, and solar lentigines behave very differently at a cellular level, so selecting the appropriate chemical peel starts with the correct diagnosis⁸,⁹.
Post acne marks
Post-inflammatory hyperpigmentation (PIH) refers to the stubborn dark spots left behind after skin inflammation or acne heals⁹. While superficial peels can help fade these surface marks by shedding melanin-laden cells, any procedure that induces excessive irritation can inadvertently trigger secondary PIH, especially in darker skin tones⁸,⁹. An additional benefit of chemical peels is the exfoliation of trapped oil and dirt, that can also improve acne.
Melasma
Chemical peels can play a supportive role in melasma management when combined with strict sun protection and medical topical therapies⁸. Clinical studies show noticeable brightening, but long-term maintenance remains challenging due to melasma’s high recurrence rate⁸.
Hormonal fluctuations, UV exposure, and genetic predisposition drive melasma from within. Expecting a strong chemical peel to “cure” melasma permanently is unrealistic. In my clinic’s pigmentation assessment guide, I explain why establishing an accurate diagnosis and patient triggers must always precede procedural interventions.
What about chemical peels for acne scars?
Indented or depressed acne scars represent structural collagen loss in the deeper dermal layer⁹. While a superficial chemical peel can smooth surface texture and fade accompanying redness or pigmentation, deeper structural scars require treatments targeted at collagen remodeling and tethered tissue breakdown⁹.
TCA CROSS (Chemical Reconstruction of Skin Scars) is a specialised focal technique, completely distinct from a standard full-face peel⁹. It involves applying high-concentration TCA precisely into the base of individual ice-pick or narrow boxcar scars to stimulate localized dermal regeneration⁹.
For other scar types such as rolling or tethered scars, modalities like subcision, radio frequency microneedling, fractional CO2 laser and ECM skinboosters and/or PDLLA skin boosters aremore appropriate⁹. You can read more about how I tailor these interventions in The Skin Longevity Clinic’s acne scar treatment guide.
Can chemical peels stimulate collagen and soften fine lines?
Chemical resurfacing can induce dermal remodeling and collagen synthesis relevant to skin aging, with results proportional to the treatment depth¹,¹⁰. However, it is important to separate surface refinement and softening of fine lines from correcting significant facial volume loss or structural skin laxity¹,¹⁰.
A 2021 study investigated a blended TCA and lactic acid formulation across enzyme assays, skin models, and donated human skin explants¹¹. Researchers observed positive changes in collagen markers and melanin regulation; however, this was laboratory-based ex vivo research rather than a clinical trial evaluating real-world facial rejuvenation in patients¹¹. While these findings provide useful insights into potential biological mechanisms, they do not guarantee specific clinical outcomes for wrinkles or pigmentation in individual patients¹¹.
Are chemical peels safe for Asian and darker skin tones?
Superficial chemical peels can be performed safely on darker skin types (Fitzpatrick types III to VI), provided precautions are taken to prevent post-inflammatory hyperpigmentation (PIH)¹². For patients, a history of reactive pigmentation, keloids, or compromised barrier function is just as important as baseline skin tone when customising a treatment plan¹⁵.
A landmark retrospective study examining 473 superficial peel treatments in Fitzpatrick skin types III to VI reported a low overall complication rate of 3.8% (18 treatments)¹². Specific observed side effects included localized crusting (2.3%), post-inflammatory hyperpigmentation (1.9%), and transient erythema (1.9%)¹².
Patients with Fitzpatrick skin type VI experienced a higher relative risk of adverse events, with an odds ratio of 5.14 (95% CI: 1.21–21.8)¹². Reassuringly, all complications resolved within eight months, and adverse events occurred less frequently during winter months in that study cohort¹².
I share these findings to highlight the importance of careful patient selection, conservative acid choices, and diligent post-care, rather than assuming superficial peels carry zero risk of pigmentation changes.
What are the side effects and risks of chemical peels?
Transient redness, mild tightness, temporary dryness, and flaking are expected post-peel responses¹. Potential complications include persistent hyperpigmentation or hypopigmentation, prolonged erythema, bacterial or fungal infection, HSV (cold sore) reactivation, and scarring¹,³.
Milia (small keratin cysts) and transient acneiform breakouts can also occur during the re-epithelialisation phase¹. Therefore, a history of cold sores, hypertrophic scarring, or abnormal wound healing should always be disclosed prior to treatment¹⁵.
A 2024 retrospective study evaluated 25 patients referred specifically for procedural complications following chemical peels, lasers, and energy-based devices¹³. Documented complications included hypertrophic scarring, tissue atrophy, and long-term dyschromia¹³. However, because this study focused exclusively on tertiary referral cases and combined multiple procedural types, it does not reflect the baseline complication rate of standard chemical peels in most outpatient clinics¹³.

This checklist summarises the medical history and skincare details to discuss before a chemical peel¹⁵. Current or recent isotretinoin use requires an individual assessment rather than an automatic exclusion from superficial peeling¹⁴.
What should be reviewed before a chemical peel?
A thorough medical consultation evaluates your suitability including active skin condition, medical history, and current topicals¹⁵. Active skin infections, broken skin, or acute eczema flares in the treatment area represent immediate contraindications to chemical peeling¹⁵.
Always inform your doctor if you are pregnant, breastfeeding, taking hormonal medications, or have recently undergone aesthetic treatments to guide pregnancy safe choices.
Retinoids and exfoliating skincare
Topical retinoids (like tretinoin, adapalene, or retinol) thin the stratum corneum and enhance peel penetration, increasing potential irritation if not managed correctly³. Expert consensus recommends pausing prescription tretinoin approximately one week prior to chemical peeling in Fitzpatrick skin types IV to VI to mitigate excessive acid penetration and PIH risk³.
This recommendation is a clinical guideline rather than an instruction to stop all prescribed treatments unadvised. Always follow tailored pre-procedure instructions according to your doctor regarding when to pause and resume your active topicals.
Recent isotretinoin treatment
The traditional practice of delaying superficial procedures for 6 to 12 months after completing oral isotretinoin has evolved. A comprehensive systematic review and expert consensus panel concluded that there is insufficient evidence to routinely delay superficial chemical peels solely due to current or recent oral isotretinoin use¹⁴.
However, this recommendation applies strictly to superficial modalities¹⁴. Your current skin barrier status, healing capacity, and overall treatment plan still require individualised medical assessment.
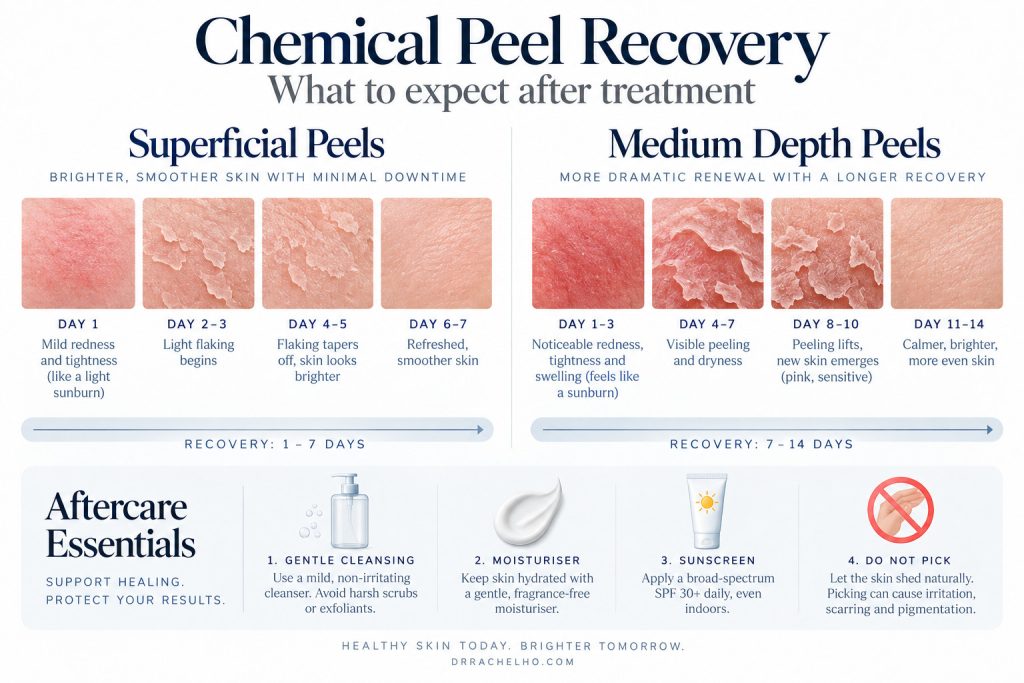
Healing commonly takes around one to seven days after a superficial peel and seven to fourteen days after a medium depth peel, with redness sometimes lasting longer¹⁷. Aftercare includes gentle cleansing, moisturising, sun protection and following advice on restarting active skincare³,¹⁵.
What recovery and results should I expect after a chemical peel?
Downtime varies directly with peel depth, and even light superficial peels can cause subtle redness, tightness, or light scaling¹⁷. Most chemical peels take approximately 1 to 7 days of healing following superficial peels, and 7 to 14 days for medium-depth peels, with mild redness sometimes lasting longer¹⁷.
It is helpful to separate “social downtime” (when you feel comfortable returning to work) from complete barrier recovery. I always advise planning clinical peels well in advance of major social events or tropical holidays to minimise disruption to your social activities.
Does more peeling mean a better result?
Visible skin shedding varies significantly between peeling formulations; many modern superficial peels produce micro-exfoliation with little to no visible peeling³.
Why aftercare for chemical peels matters
Strict broad-spectrum sun protection before and after treatment is vital to control pigment risk, while gentle cleansing and barrier-supportive moisturizers facilitate smooth repair³,¹⁵. Picking at peeling skin or reintroducing active exfoliants prematurely can disrupt healing and trigger scarring or hyperpigmentation¹⁵,¹⁷.My skin barrier guide also offers practical tips on maintaining skin health post-treatment.
For step-by-step guidance on pre-peel preparation, post-care products, makeup application, and follow-up schedules, refer to The Skin Longevity Clinic’s chemical peel treatment and recovery guide.
Are chemical peels worth it?
Before deciding on whether a chemical peel is worth it, I always advise starting with a clear, defined skin objective and evaluating how a peel compares to alternative treatment options,, such as lasers or other resurfacing skin treatments. For active acne, this means weighing chemical peels against topical and oral medical therapies; for melasma, comparing them with pico lasers; and for acne scars, matching the technique to your specific scar anatomy⁷,⁸,⁹. During the consultation, ask your doctor why a specific peeling agent and depth were selected to set realistic expectations about results and understand protocols for managing recovery.
My takeaway on chemical peels
With the plethora of cutting edge devices and technologies in the aesthetic field, chemical peels can feel outdated. Nonetheless, chemical peels are a valuable, highly versatile tool in modern aesthetic dermatology, and are a cornerstone for treating hyperpigmentation, acne, congestion and dullness in my clinic for reliability and affordability.
References
- O’Connor AA, Lowe PM, Shumack S, Lim AC. Chemical peels: A review of current practice. Australasian Journal of Dermatology. 2018;59(3):171 to 181. doi:10.1111/ajd.12715. PubMed
- Soleymani T, Lanoue J, Rahman Z. A Practical Approach to Chemical Peels: A Review of Fundamentals and Step by Step Algorithmic Protocol for Treatment. Journal of Clinical and Aesthetic Dermatology. 2018;11(8):21 to 28. PubMed Central (PMC)
- Lee KC, Wambier CG, Soon SL, et al. Basic chemical peeling: Superficial and medium depth peels. Journal of the American Academy of Dermatology. 2019;81(2):313 to 324. doi:10.1016/j.jaad.2018.10.079. Peeling Society
- Lober CW. Chemexfoliation: Indications and cautions. Journal of the American Academy of Dermatology. 1987;17(1):109 to 112. doi:10.1016/S0190-9622(87)70181-9. PubMed
- Kontochristopoulos G, Platsidaki E. Chemical peels in active acne and acne scars. Clinics in Dermatology. 2017;35(2):179 to 182. doi:10.1016/j.clindermatol.2016.10.011. PubMed
- Chen X, Wang S, Yang M, Li L. Chemical peels for acne vulgaris: A systematic review of randomised controlled trials. BMJ Open. 2018;8:e019607. doi:10.1136/bmjopen-2017-019607. PubMed Central (PMC)
- Reynolds RV, Yeung H, Cheng CE, et al. Guidelines of care for the management of acne vulgaris. Journal of the American Academy of Dermatology. 2024;90(5):1006.e1 to 1006.e30. doi:10.1016/j.jaad.2023.12.017. The Academy’s accompanying summary confirms the insufficient evidence for procedural recommendations. American Academy of Dermatology
- Sarkar R, Bansal S, Garg VK. Chemical Peels for Melasma in Dark Skinned Patients. Journal of Cutaneous and Aesthetic Surgery. 2012;5(4):247 to 253. doi:10.4103/0974-2077.104912. JCAS
- Gupta A, Kaur M, Patra S, Khunger N, Gupta S. Evidence Based Surgical Management of Post Acne Scarring in Skin of Color. Journal of Cutaneous and Aesthetic Surgery. 2020;13(2):124 to 141. doi:10.4103/JCAS.JCAS_154_19. JCAS
- Kaltchenko MV, Chien AL. Photoaging: Current Concepts on Molecular Mechanisms, Prevention, and Treatment. American Journal of Clinical Dermatology. 2025;26(3):321 to 344. doi:10.1007/s40257-025-00933-z. PubMed
- Bhardwaj V, Sharma K, Maksimovic S, et al. Professional Grade TCA Lactic Acid Chemical Peel: Elucidating Mode of Action to Treat Photoaging and Hyperpigmentation. Frontiers in Medicine. 2021;8:617068. doi:10.3389/fmed.2021.617068. Frontiers
- Vemula S, Maymone MBC, Secemsky EA, et al. Assessing the safety of superficial chemical peels in darker skin: A retrospective study. Journal of the American Academy of Dermatology. 2018;79(3):508 to 513.e2. doi:10.1016/j.jaad.2018.02.064. PubMed
- Murray TN, Lohray R, Schultz KP, Boutros S, Friedman PM. Complications of Chemical Peels, Lasers, and Energy Based Device Procedures Performed by Core Cosmetic Physicians: A Retrospective Analysis. Lasers in Surgery and Medicine. 2024;56(7):619 to 624. doi:10.1002/lsm.23820. Houston Methodist Scholars
- Spring LK, Krakowski AC, Alam M, et al. Isotretinoin and Timing of Procedural Interventions: A Systematic Review With Consensus Recommendations. JAMA Dermatology. 2017;153(8):802 to 809. doi:10.1001/jamadermatol.2017.2077. JAMA Network
- Khunger N; IADVL Task Force. Standard guidelines of care for chemical peels. Indian Journal of Dermatology, Venereology and Leprology. 2008;74 Supplement:S5 to S12. IJDVL
- Raef H, Brody HJ, Monheit GD, Coleman WP. A History of the Advances in Chemical Peeling in Dermatologic Surgery Since 2000. Dermatologic Surgery. 2025;51(9):831 to 840. doi:10.1097/DSS.0000000000004792. PubMed
- American Academy of Dermatology. Chemical peels: FAQs. Patient guidance on healing, recovery and aftercare. AAD

No Comments