


19 Oct Tranexamic Acid for Melasma: Topical and Oral Evidence
Tranexamic Acid for Melasma: Topical and Oral Evidence
By Dr Rachel Ho| Updated September 30, 2026
When patients come to see me about melasma, tranexamic acid is often one of the first ingredients they ask about. Tranexamic has generated immense interest in the aesthetic field, and for good reason: oral tranexamic acid consistently offers some of our strongest clinical evidence for melasma when prescribed to appropriately selected patients1,6.
However, tranexamic acid isn’t necessarily only available as an oral medication. Topical serums, micro-injections, and procedure-assisted delivery methods for tranexamic acid have all been widely studied, although their actual results and safety profiles vary considerably6,7,12,13.
In treating hyperpigmentation and selecting patients for tranexamic acid therapy in my clinic, I evaluate the exact diagnosis, past response to treatments, and complete medical history before recommending a specific route for tranexamic acid. It is also crucial to understand the treatments that can specifically target my patients’ type of hyperpigmentation based on the evidence for best results.
This article breaks down how tranexamic acid works across different delivery methods and my personal review of tranexamic acid serum, SkinCeuticals Discolouration Defense. For a more in-depth read to hyperpigmentation, you can read my guide to what I look for before treating hyperpigmentation. My skincare guide for hyperpigmentation also discusses the principles of how to pair skincare synergistically to treat dark spots.
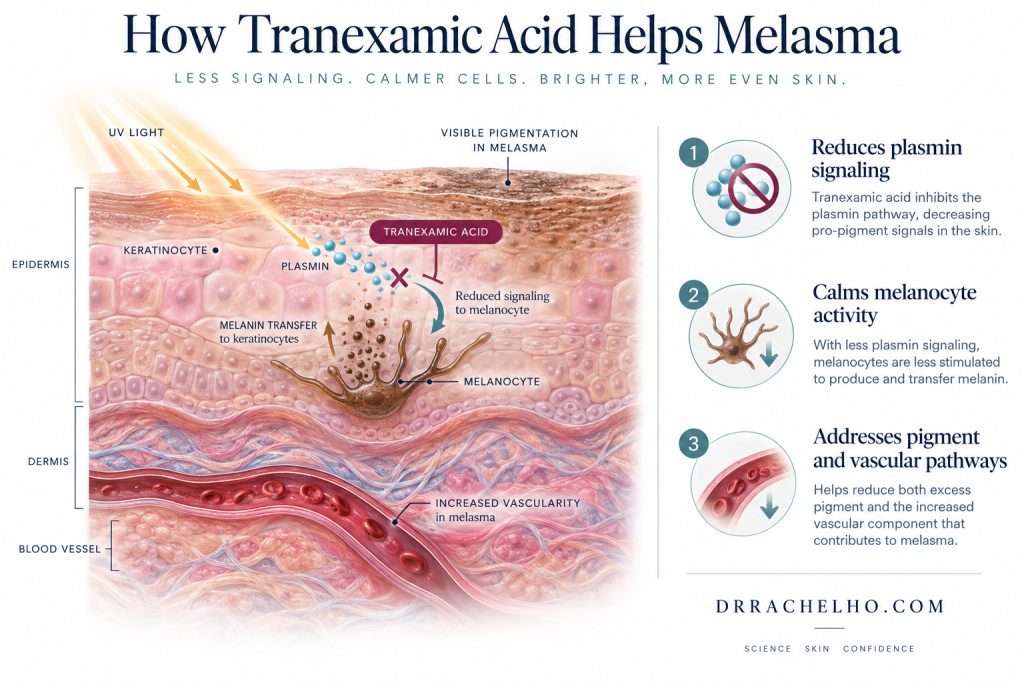
Tranexamic acid acts on plasmin related signalling involved in stimulating melanin production¹. This differs from exfoliating acids, which act on superficial skin cells¹.
What is tranexamic acid?
Tranexamic acid is a synthetic derivative of the amino acid lysine1. Tranexamic acid is is primarily used as an antifibrinolytic medication to reduce the breakdown of blood clots to manage heavy bleeding conditions19.
In dermatology, oral tranexamic acid is used “off-label” for melasma, which simply means this specific aesthetic application falls outside its original licensed indication9,18. Unlike exfoliating acids (such as glycolic or salicylic acid) that peel away surface cells, tranexamic acid works deeper within the skin by altering cellular signalling pathways1. If you’re interested in understanding chemical exfoliation, please my guides to chemical exfoliation with acids and seperately, salicylic acid skincare guide.
How does tranexamic acid reduce pigmentation?
Tranexamic acid reduces signals that trigger melanocytes
When your skin is exposed to ultraviolet (UV) light, it increases local plasmin activity1. Plasmin acts as a trigger, kicking off a chain reaction that stimulates melanocytes i.e. the cells that produce melanin, which is responsible for hyperpigmentation1.
Tranexamic acid works by blocking plasminogen binding and activation, essentially cutting off the signal before it can trigger downstream inflammatory pathways involving arachidonic acid and alpha-melanocyte-stimulating hormone (-MSH)1.
What newer laboratory research reveals about tranexamic acid for treatment of hyperpigmentation
Recent studies have uncovered even more layers to how tranexamic acid interacts with our skin cells:
• Keratinocyte Signalling (2022): A laboratory study showed that tranexamic acid increases the secretion of a protein called transforming growth factor beta 1 (TGF-1) from surface skin cells (keratinocytes)2. This signal tells underlying melanocytes to downregulate key pigment-producing enzymes, including tyrosinase, MITF, and TRP-12.
• Hormonal Pathways (2025): Another lab study demonstrated that tranexamic acid can suppress pigment formation stimulated by 17-estradiol (a form of estrogen) through the PKA/CREB/MITF signalling pathway3. While this helps explain why tranexamic acid works so well for hormonally driven melasma, it is important to note that tranexamic acid does not alter systemic hormone levels in your body3.
Tranexamic acid addresses the vascular component of melasma
One of the reasons melasma is regarded as a complex type of hyperpigmentation is because it often has a vascular component, where abnormally dilated blood vessels supply the hyperpigmentation17. One small study evaluating skin biopsies from participants using combined oral and topical tranexamic acid showed a noticeable reduction in epidermal pigment, blood vessel density, and inflammatory mast cells17. Although these biopsies were taken from just eight participants, they highlight how tranexamic acid targets both pigment and redness simultaneously17.

Research on tranexamic acid for melasma includes different delivery routes, formulations and comparison treatments⁴,⁷,¹²–¹⁴,¹⁶,²⁰. A study of a combination serum evaluates the complete formulation and cannot isolate the contribution of tranexamic acid alone²⁰.
Evidence for tranexamic acid: What do the studies actually test?
When evaluating research, remember that a clinical result for an oral medication cannot be extrapolated for atopical serum, nor can a multi-ingredient cream establish the efficacy of tranexamic acid on its own6,12. These are the concentrations and protocols of tranexamic acid in scientific trials that have been published:
Studies on tranexamic acid and melasma
| Route and study | Treatment and comparison | Main finding | Important limitation |
|---|---|---|---|
| Oral tranexamic acid(Del Rosario, 2018) | 44 participants; 250 mg twice daily for 3 months vs. placebo (both used sunscreen) | Melasma severity score fell by 49% with tranexamic acid vs. 18% with placebo4. | Measures overall severity reduction, not a total cure; small trial size4. |
| Topical tranexamic acid(Ebrahimi, 2014) | 3% tranexamic acid vs. 3% hydroquinone + 0.01% dexamethasone split-face for 12 weeks | Both sides improved similarly; tranexamic acid caused fewer adverse side effects14. | Hydroquinone product used was weaker than standard 4% hydroquinone triple combination cream14. |
| Topical tranexamic acid(Kanechorn Na Ayuthaya, 2012) | 23 women; 5% tranexamic acid vs. plain vehicle split-face for 12 weeks | Both sides improved, with no statistically significant difference between them13. | This specific 5% formulation failed to outperform its base vehicle cream13. |
| Tranexamic acid + Niacinamide(Ghasemiyeh, 2025) | Niosomal 2% tranexamic acid + 2% niacinamide vs. conventional 5% tranexamic acid + 4% niacinamide vs. 4% hydroquinone | All groups improved similarly; hydroquinone caused more adverse reactions12. | Tested specific combined formulations with short follow-up; absence of difference does not equal equivalence12. |
| Intradermal tranexamic acid(El Hadidi, 2021) | 45 women; oral 250 mg twice daily vs. micro-injections (4 mg/mL or 100 mg/mL) every 2 weeks | All groups improved without significant differences between routes7. | Small sample size and short 8-week timeframe7. |
| Microneedling(Arida, 2021) | 20 patients; 3 monthly microneedling sessions with tranexamic acid on one side, placebo on the other | Adding topical tranexamic acid provided no significant advantage over microneedling alone16. | Highlights the need to evaluate procedure effects separately from active topicals16. |
| Combination Serum(Desai, 2019) | 12-week trial of a serum containing 3% tranexamic acid, 1% kojic acid, and 5% niacinamide | Statistically significant improvements in melasma and overall skin clarity20. | Evaluates the combined product; cannot isolate the individual effect of tranexamic acid20. |

Oral tranexamic acid may be considered as an additional treatment for selected patients with persistent melasma⁸,⁹. Medical assessment should include clotting history, current medicines, kidney function and pregnancy plans¹⁸,¹⁹. \
Oral tranexamic acid for melasma
How effective is it?
Oral tranexamic acid has strong clinical backing as an adjunct therapy for stubborn melasma that does not improve with topical treatments8,9. A comprehensive meta-analysis of 24 randomised controlled trials confirmed that oral tranexamic acid provides a far more consistent improvement to standard melasma routines than topical or injected versions6.
In the landmark Del Rosario trial, the 49% improvement measured the modified Melasma Area and Severity Index (mMASI), a score reflecting the darkness and surface area of the pigmentation4.
In Singapore, a retrospective study of 561 patients found that 89.7% showed visible clearance (typically within two months), though 27.2% experienced a relapse over time5.
Does a higher dose of tranexamic acid yield better results for melasma treatment?
A higher dose of tranexamic acid does not necessarily yield better melasma reduction. A trial comparing 250 mg twice daily against a higher dose of 500 mg twice daily found virtually identical efficacy over 12 weeks15. This is precisely why I tailor the dosage to the individual patient rather than assuming that a higher dose is more effective.
What are the risks and side effects of tranexamic acid for melasma?
Common side effects of oral tranexamic acid include mild stomach upset, nausea, headaches, and lighter menstrual periods11. Because tranexamic acid affects blood clotting pathways, systemic blood clot risk (thromboembolism) is the primary medical consideration9,18.
While large safety reviews such as the Singapore series of 561 patients and a 2024 review of 206 patients show very low rates of adverse vascular events, the risk is not zero5,10.
As a medical standard, expert consensus guidelines strictly advise against oral tranexamic acid if you have a personal or family history of thromboembolic disease, or if you are currently taking combined oral contraceptive pills18. During a consultation, I thoroughly review your medical history, including kidney function, current medications, and any plans for pregnancy18,19.
When to seek immediate help: If you are taking oral tranexamic acid and experience sudden, unexplained shortness of breath, painful swelling in your leg, or visual disturbances, you should stop the medication immediately and seek urgent medical care19.

Topical tranexamic acid studies have produced differing results, making the exact formulation important when interpreting the evidence¹²–¹⁴. Dryness, flaking or irritation can occur, so tolerability also matters when introducing a serum¹¹,¹³. Pasted markdown
Topical tranexamic acid for melasma and dark spots
Why do serum and cream studies show conflicting results?
Topical tranexamic acid has been studied in strengths ranging from 2% to 10% across various gels, creams, and liposomal delivery systems1. The varying trial results above illustrate that a serum’s effectiveness depends heavily on its overall formulation, stability, and delivery vehicle and not just the percentage on the label12,13,14. For example, a study using advanced “niosomes” (microscopic capsules that help ingredients penetrate the skin) cannot be used to prove that a standard water-based serum will perform in a similar manner and yield the same results12.
When choosing a serum, look for a well-formulated product that plays nicely with your existing skincare. My guide to hyperpigmentation skincare breaks down how tyrosinase inhibitors, niacinamide, and exfoliants work together.
Potential side effects of topical tranexamic acid
While topical tranexamic acid is generally well-tolerated, it can occasionally cause localised dryness, flaking, or mild irritation11,13. I recommend introducing any new active serum gradually so you can easily monitor how your skin responds.

My review of SkinCeuticals Discolouration Defense
The formula I tested combined 3% tranexamic acid, 5% niacinamide, and 1% kojic acid20. Based on this ingredient list, this formula makes lightening of hyperpigmentation plausible because each ingredient addresses a different step in the pigmentation process1,20. I’ve previously discussed niacinamide in detail in my niacinamide skincare guide.
My personal experience with SkinCeuticals Discolouration Defense
I initially purchased this serum due to its widespread popularity in the aesthetic community. However, after consistent, dedicated use, my own dark spots and melasma remained visibly unchanged. Having previously achieved excellent brightening results with simple over-the-counter vitamin C serums, this was disappointing. I’ve also discussed this ingredient in greater detail in my vitamin C skincare guide.
Additionally, I didn’t experience the soothing or oil-balancing benefits I usually enjoy with niacinamide formulations.
Would I repurchase it SkinCeuticals Discolouration Defense again?
Personally, I would not repurchase it. Far more affordable products have delivered better clinical outcomes for my skin.

Microneedling assisted delivery of tranexamic acid has been studied for melasma¹⁶,²². In one trial, adding tranexamic acid provided no significant advantage over microneedling with placebo, highlighting why the procedure and ingredient should be evaluated separately¹⁶.
Intradermal tranexamic acid injections
Intradermal therapy involves micro-injecting tiny quantities of liquid tranexamic acid directly into the pigmented areas of the dermis during an in-clinic procedure7.
While an 8-week study showed comparable improvement between oral tranexamic acid and micro-injections, broader systematic reviews reveal mixed outcomes6,7,8. Injections do come with localized side effects like temporary pain, swelling, and bruising at the injection sites11.
Microneedling and assisted delivery of tranexamic acid
Assisted delivery uses procedural tools like microneedling or fractional lasers to create microscopic channels in the skin, allowing topical tranexamic acid to penetrate deeper1,16,22.
It is important to look at how these studies are designed:
• Microneedling + tranexamic acid vs. Sham: A 2017 study showed that microneedling paired with a 0.5% tranexamic acid solution delivered significantly better fading than a sham procedure22.
• Microneedling + tranexamic acid vs. Microneedling alone: Conversely, a 2021 trial treated both sides of the face with microneedling, adding tranexamic acid to one side and a placebo to the other. This study found no additional benefit from adding the tranexamic acid solution16. This proves that much of the visual improvement actually stems from the microneedling procedure itself stimulating skin renewal, rather than the topical liquid applied on top16.
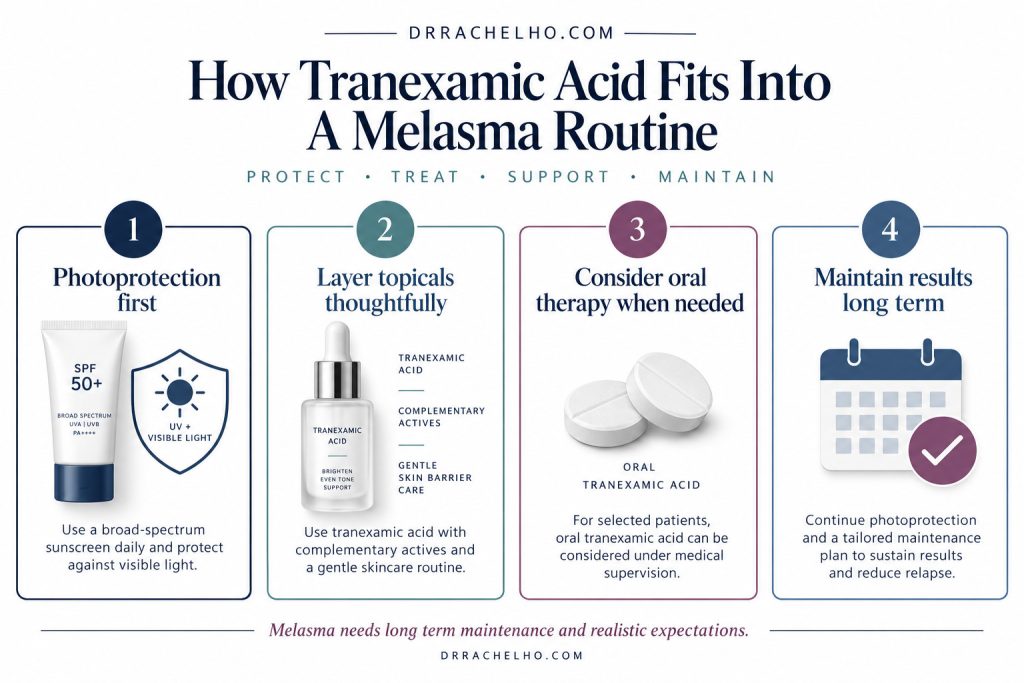
Tranexamic acid fits within a melasma plan that includes photoprotection, suitable skincare and ongoing maintenance⁸,¹⁸,²¹. Oral treatment may be considered for selected patients after medical assessment, while the routine is reviewed according to response⁸,⁹.
How should tranexamic acid fit into your melasma routine?
1. Photoprotection comes first: Strict sun protection remains the absolute cornerstone of any melasma treatment plan8,18. Broad-spectrum sunscreens shield against UV rays, while iron-oxide-tinted sunscreens protect against visible light—a major trigger for melasma in deeper skin tones21. Explore my clinic’s guide to sunscreen for melasma for tips and recommendations.
2. Layer topicals intelligently: A topical tranexamic acid serum can be a helpful, gentle addition to your daily morning or evening routine, working alongside tyrosinase inhibitors like azelaic acid or hydroquinone12,20. Please refer to my azelaic acid guide for more about this ingredient.
3. Medical supervision for oral therapy: If topical skincare isn’t delivering sufficient results, an oral tranexamic acid prescription can be considered after a thorough clinical assessment8,9.
Frequently asked questions about tranexamic acid
How long does tranexamic acid take to work?
Most clinical trials evaluate results over an 8- to 12-week timeframe4,7,13. In the Singapore oral tranexamic acid study, most patients began noticing visible fading within two months5. This provides a realistic timeline for reviewing your progress.
Can tranexamic acid permanently cure melasma?
Unfortunately, no treatment can offer a permanent cure for melasma. Because melanocytes remain sensitive to sun and hormonal shifts, melasma can recur after stopping tranexamic acid4,5. Long-term maintenance and rigorous sun protection are essential to preserving your results8.
Can I use tranexamic acid together with niacinamide?
Yes you can use tranexamic acid and niacinamide together. Both active ingredients work via completely different, complementary mechanisms. Tranexamic acid calms pigment production pathways, while niacinamide blocks pigment transfer to surface cells1,12. They are frequently formulated together in serums20.
Does tranexamic acid help with post-acne dark marks?
While tranexamic acid is most famous for melasma, combination serums containing tranexamic acid have shown success in treating post-inflammatory hyperpigmentation (PIH) left behind by acne breakouts20.
My perspective on tranexamic acid for melasma treatment in Singapore
Tranexamic acid is a helpful treatment for melasma provided it is used for the right diagnosis, via the correct route, and with realistic expectations. For a deeper look into how I treat melasma in the clinic please refer to The Skin Longevity Clinic’s guide to melasma treatment in Singapore. My goal is always to create a safe, evidence-based strategy tailored to your skin.
References
1. Gan C, Rodrigues M. An Update on New and Existing Treatments for the Management of Melasma. American Journal of Clinical Dermatology. 2024;25(5):717–733. DOI: 10.1007/s40257-024-00863-2.
2. Xing X, Xu Z, Chen L, Jin S, Zhang C, Xiang L. Tranexamic acid inhibits melanogenesis partially via stimulation of TGF-β1 expression in human epidermal keratinocytes. Experimental Dermatology. 2022;31(4):633–640. DOI: 10.1111/exd.14509.
3. Bae YJ, Lee EJ, Kim JY, et al. Tranexamic Acid Inhibits 17β-Estradiol-Induced Melanogenesis Through PKA/CREB/MITF Pathway. Experimental Dermatology. 2025;34(12):e70194. DOI: 10.1111/exd.70194.
4. Del Rosario E, Florez-Pollack S, Zapata L Jr, et al. Randomized, placebo-controlled, double-blind study of oral tranexamic acid in the treatment of moderate-to-severe melasma. Journal of the American Academy of Dermatology. 2018;78(2):363–369. DOI: 10.1016/j.jaad.2017.09.053.
5. Lee HC, Thng TGS, Goh CL. Oral tranexamic acid (TA) in the treatment of melasma: A retrospective analysis. Journal of the American Academy of Dermatology. 2016;75(2):385–392. DOI: 10.1016/j.jaad.2016.03.001.
6. Feng X, Su H, Xie J. Efficacy and safety of tranexamic acid in the treatment of adult melasma: An updated meta-analysis of randomized controlled trials. Journal of Clinical Pharmacy and Therapeutics. 2021;46(5):1263–1273. DOI: 10.1111/jcpt.13430.
7. El Hadidi H, Mosaad R, Ragab N. The efficacy of oral vs different dilutions of intradermal tranexamic acid microinjections in melasma: A randomized clinical trial. Dermatologic Therapy. 2021;34(3):e14924. DOI: 10.1111/dth.14924.
8. McKesey J, Tovar-Garza A, Pandya AG. Melasma Treatment: An Evidence-Based Review. American Journal of Clinical Dermatology. 2020;21(2):173–225. DOI: 10.1007/s40257-019-00488-w.
9. Bala HR, Lee S, Wong C, Pandya AG, Rodrigues M. Oral Tranexamic Acid for the Treatment of Melasma: A Review. Dermatologic Surgery. 2018;44(6):814–825. DOI: 10.1097/DSS.0000000000001518.
10. Hashemi DA, Wang JV, Geronemus RG. Potential Role of Tranexamic Acid and Nonablative Fractional Resurfacing in Managing Facial Hyperpigmentation. JAMA Dermatology. 2024;160(2):239–240. Correspondence. DOI: 10.1001/jamadermatol.2023.5470.
11. Zhang L, Tan WQ, Fang QQ, et al. Tranexamic Acid for Adults with Melasma: A Systematic Review and Meta-Analysis. BioMed Research International. 2018;2018:1683414. DOI: 10.1155/2018/1683414.
12. Ghasemiyeh P, Haghighi NF, Dastgheib L, Ranjbar S, Mohammadi-Samani S. Safety and efficacy of niosomal and conventional tranexamic acid/niacinamide vs. hydroquinone creams in melasma: A randomized, double-blind, case-controlled clinical trial. Scientific Reports. 2025;15:42739. DOI: 10.1038/s41598-025-26693-8.
13. Kanechorn Na Ayuthaya P, Niumphradit N, Manosroi A, Nakakes A. Topical 5% tranexamic acid for the treatment of melasma in Asians: a double-blind randomized controlled clinical trial. Journal of Cosmetic and Laser Therapy. 2012;14(3):150–154. DOI: 10.3109/14764172.2012.685478.
14. Ebrahimi B, Naeini FF. Topical tranexamic acid as a promising treatment for melasma. Journal of Research in Medical Sciences. 2014;19(8):753–757. PMID: 25422661.
15. Bhattacharjee R, Hanumanthu V, Thakur V, et al. A randomized, open-label study to compare two different dosing regimens of oral tranexamic acid in treatment of moderate to severe facial melasma. Archives of Dermatological Research. 2023;315(6):1831–1836. DOI: 10.1007/s00403-023-02549-x.
16. Kuster Kaminski Arida D, Orso Rebellato PR, Marioto de Campos GL, et al. Randomized, double-blind, placebo-controlled split-face trial of the efficacy of tranexamic acid by drug delivery through microneedling in the treatment of melasma. Journal of Cosmetic Dermatology. 2021;20(12):4005–4010. DOI: 10.1111/jocd.14257.
17. Na JI, Choi SY, Yang SH, Choi HR, Kang HY, Park KC. Effect of tranexamic acid on melasma: a clinical trial with histological evaluation. Journal of the European Academy of Dermatology and Venereology. 2013;27(8):1035–1039. DOI: 10.1111/j.1468-3083.2012.04464.x.
18. Godse K, Sarkar R, Mysore V, et al. Oral Tranexamic Acid for the Treatment of Melasma: Evidence and Experience-Based Consensus Statement from Indian Experts. Indian Journal of Dermatology. 2023;68(2):178–185. DOI: 10.4103/ijd.ijd_266_22.
19. HealthHub Singapore. Tranexamic Acid (Oral). Official patient medication information. Accessed 30 September 2026. Medication information.
20. Desai S, Ayres E, Bak H, et al. Effect of a Tranexamic Acid, Kojic Acid, and Niacinamide Containing Serum on Facial Dyschromia: A Clinical Evaluation. Journal of Drugs in Dermatology. 2019;18(5):454–459. PMID: 31141852.
21. Castanedo-Cazares JP, Hernandez-Blanco D, Carlos-Ortega B, Fuentes-Ahumada C, Torres-Álvarez B. Near-visible light and UV photoprotection in the treatment of melasma: a double-blind randomized trial. Photodermatology, Photoimmunology & Photomedicine. 2014;30(1):35–42. DOI: 10.1111/phpp.12086.
22. Xu Y, Ma R, Juliandri J, et al. Efficacy of functional microarray of microneedles combined with topical tranexamic acid for melasma: A randomized, self-controlled, split-face study. Medicine. 2017;96(19):e6897. DOI: 10.1097/MD.0000000000006897.

No Comments